Mimrylo (rusfertide) is the first FDA-approved treatment that mimics the iron-regulating hormone hepcidin, giving adults with polycythemia vera a new way to control excess red-cell production. In the phase 3 VERIFY trial, 76.9% on Mimrylo met the defined clinical-response endpoint versus 32.9% on placebo, but that result does not mean the drug is a cure or appropriate for every patient.
The Food and Drug Administration approved the medicine on Aug. 28, 2026, for treatment of erythrocytosis in adults with polycythemia vera, or PV. The agency’s announcement presents it as a new option when disease has not been adequately controlled with existing therapy. Those two formulations are important together: this is a labeled medicine for a defined condition, not a general treatment for anyone with an elevated blood count.
This explainer describes the approval evidence. It cannot determine eligibility, replace the current prescribing information, or recommend a treatment change for an individual.
Why controlling red-cell production matters
PV is a rare chronic blood cancer in which the body makes too many red blood cells. The excess can increase hematocrit, the proportion of blood made up of red cells, and make blood thicker. FDA links the disease to increased risk of cardiovascular complications including blood clots, stroke, and heart attack.
A central management target is keeping hematocrit below 45%. Phlebotomy has long been one way to reduce the red-cell burden: blood is removed from a vein as treatment. Other therapies can be used according to a patient’s risk and clinical circumstances.
The population behind the Mimrylo approval was more specific than “all adults with PV.” VERIFY enrolled adults who had needed frequent phlebotomies despite standard-of-care treatment. That context explains both why a different mechanism was attractive and why the trial percentage should not be transferred automatically to a person with a different history.
Frequent blood removal is not just a number on a chart. It requires appointments, venous access, monitoring, and repeated decisions about when another procedure is needed. Reducing that burden while maintaining hematocrit control is therefore a meaningful outcome. It is still only one part of living with a chronic disease, not evidence that all risks or symptoms disappear.
What mimicking hepcidin is designed to do
Iron is essential for making hemoglobin and new red blood cells. Hepcidin is a hormone that regulates how iron moves through and becomes available in the body. Rusfertide is designed to imitate that signal, limiting iron availability for red-cell production.

That differs conceptually from removing blood after excess cells have accumulated. It also differs from claiming that iron is simply “bad” in PV. Iron remains biologically necessary, and treatment requires monitoring. A mechanism explains the intended action of a medicine; it does not establish the right dose, combination, or risk balance for a particular person.
The “first” in FDA’s announcement refers to this hepcidin-mimicking approach in approved PV treatment. It should not be stretched into “first effective treatment,” “best treatment,” or “replacement for phlebotomy and all existing medicines.” Those are different claims and are not supported by the approval headline.
What VERIFY tested
VERIFY is a multicenter, randomized, double-blind, placebo-controlled phase 3 study identified as NCT05210790. It enrolled 293 adults with PV who required frequent phlebotomies while receiving current standard care. Participants were assigned to rusfertide or placebo in addition to that care during the controlled period.
The main effectiveness measure examined clinical response during weeks 20 through 32. In practical terms, participants needed to avoid meeting the trial’s criteria for phlebotomy while maintaining hematocrit control. FDA reports that 76.9% in the Mimrylo group met the endpoint, compared with 32.9% in the placebo group.
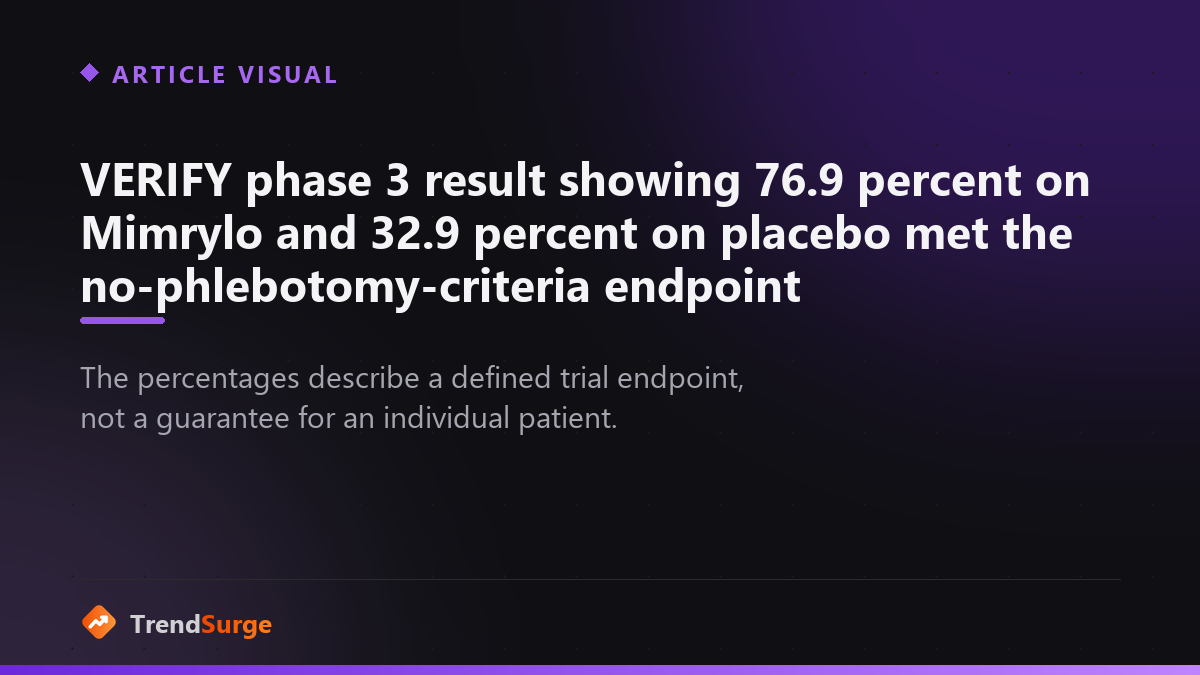
The 44-percentage-point difference is substantial inside that study. Four limits keep it interpretable.
First, the participants were selected for ongoing phlebotomy needs despite existing care. Second, the primary comparison covered a specified interval in a controlled trial. Third, “clinical response” was an endpoint with preset rules; it did not mean remission or freedom from all treatment. Fourth, a group average cannot predict whether one person will benefit or experience harm.
The Journal of Clinical Oncology abstract and ClinicalTrials.gov record supply more trial context than an approval press release, while the FDA decision establishes the U.S. regulatory action. Takeda’s announcement adds the sponsor’s account and should be read as a company source, not independent clinical guidance.
The sources answer different questions. FDA confirms what was approved and summarizes the agency’s benefit-risk decision. The trial registry records the planned study design and status. The journal abstract reports the controlled comparison, and the manufacturer explains its product program. Agreement on the headline result strengthens verification, but multiple pages do not turn sponsor-generated evidence into several independent trials.
Safety information has a hard boundary
FDA’s announcement lists injection-site reactions and anemia as the most common adverse reactions. The trial report provides percentages and additional findings, but neither a news release nor this article is a substitute for the current FDA-approved prescribing information.
That boundary matters because treatment decisions include contraindications, warnings, monitoring, concurrent medicines, pregnancy considerations, dose adjustments, and what to do after an adverse event. A concise explainer cannot safely reconstruct all of those instructions, and label information can be updated after approval.
Anyone with PV should discuss the approved label, their hematocrit history, phlebotomy burden, other treatments, and personal risks with a licensed clinician. Do not stop phlebotomy, change another medicine, or seek a dose based on this article. Patients who experience a new or concerning symptom should use the care instructions provided by their medical team.
What genuinely changed on Aug. 28
The approval added a first-in-class pathway to the U.S. PV treatment landscape. Instead of relying only on removing accumulated cells or other established strategies, clinicians now have an approved option intended to regulate the iron supply used for new red-cell production.
For adults repeatedly reaching phlebotomy criteria despite standard care, that could reduce a persistent treatment burden. The phase 3 result supports that possibility; it does not establish indefinite benefit, comparative superiority over every alternative, or the same balance for lower-risk and higher-risk patients.
The next evidence will come from broader and longer use. VERIFY includes ongoing follow-up, and post-approval pharmacovigilance can surface uncommon adverse events or practical issues that a 293-person controlled study is not designed to settle. Future comparative studies may clarify where the drug fits among available strategies.
Longer follow-up is particularly important for a chronic disease because a 12-week primary assessment window cannot answer every question about durability. It can support the defined approval endpoint without forecasting years of response for an individual.
FDA granted the application Priority Review and approved it for Takeda Pharmaceuticals America. Priority Review shortens the agency’s review goal when program criteria are met; it does not mean clinical safeguards were waived or that an approved product is automatically the preferred choice.
For another official-source health explainer, see when to get the 2026 flu shot. Our Social Security 2032 trust-fund explainer offers a nonmedical example of why a percentage needs its population and time window, and the Cuisinart grill-brush recall guide shows the different action boundary for a consumer-safety notice.
This article reflects the FDA action and source material available on Aug. 31, 2026. Prescribing and patient decisions should use the current official label and clinician guidance, not an archived news summary.


